


Background: Serious Adverse Drug Reactions (sADRs) are one of the important causes of morbidity and mortality. In India, pharmacovigilance practices are evolving but comprehensive regional data on sADRs is lacking. Understanding how sADR prevalence in India compares with global patterns is essential to improve patient safety.
Aims and Objectives: This study aimed to compare the prevalence of selected sADRs associated with commonly used drugs in India and other countries, and to examine the contributing factors.
Materials and Methods: A list of drugs was compiled using a generic drug index. A PubMed search was conducted to estimate the prevalence of sADRs in the Indian patient population. Additional data were obtained from Indian Pharmacopoeia Commission publications and FAERS (FDA Adverse Event Reporting System) database. Data was extracted and tabulated for comparison.
Results: Twenty-two studies (including FAERS data) met the inclusion criteria, and ten drugs with their sADRs were selected for comparison. Indian patients exhibited a higher prevalence of several sADRs-for example, Linezolid-induced neuropathy (93.3% in India vs. 1.6% globally) and Non Steroidal Anti-Inflammatory Drugs (NSAID)-induced nephrotoxicity (27.88% vs. 13%). Lamivudine-induced hearing loss and Pioglitazone-induced bladder cancer showed significantly lower rates of sADRs in Indian studies.
Conclusion: Marked differences in the prevalence of sADRs between India and other countries highlight the need for sensitising physicians to these differences and associated implications in prescribing and patient management.
Abstract
Share on Mobile
Scan to access on mobile
Keywords
Adverse Drug Reaction
Adverse Effect
India
Pharmacovigilance
Prevalence
INTRODUCTION
Adverse Drug Reactions (ADRs) are one of the significant causes of morbidity and mortality. Serious adverse drug reactions (sADRs) warrant particular attention in both clinical care and research settings. Robust pharmacovigilance systems and reliable sADR reporting mechanisms are essential components of clinical research and healthcare delivery. A meta-analysis covering 18,818 hospitalised patients globally estimated a pooled ADR incidence of 16.88% (Miguel et al., 2012), while another involving over 1.5 million patients in primary care settings reported a prevalence of 8.32% (Insani et al., 2021). In an Indian study, ADRs accounted for 6.89% of all admissions (Patel et al., 2007). However, ADR prevalence varies widely across settings and geographies.
In India, the Pharmacovigilance Programme of India (PvPI) has brought ADR reporting and analysis in line with global standards. However, the data lacks an all-inclusive analysis to understand the prevalence of ADRs in the genetically and ethnically diverse Indian population for the majority of drugs. Moreover, open access to this data is not available for research in this domain. Thus, global comparisons are drawn with published literature in this context.
The aims and objectives of our study were
The aims and objectives of our study were
• To compile and analyse the prevalence and patterns of serious ADRs in India with those in other countries for commonly prescribed drugs.
• To explore systemic and biological factors contributing to these variations.
METHODOLOGY
Study design
This study aimed at comparing the prevalence of sADRs associated with commonly used drugs in India with international data by ecological study design.
Ethical statement
As this study relies on previously published literature and publicly available data from the FAERS database, ethical approval was not required.
Search strategy
A list of systemically used oral drugs was compiled from previously published literature that reported ADRs in the Indian population, excluding fixed drug combinations, ayurvedic preparations and nutraceuticals. PubMed search was conducted to identify all studies published between 1 January 1994 and 1 January 2024 using keywords 'Drug' , ' Adverse effect' , ' ADR' , ' Adverse Reaction' , ' Adverse Drug Reaction' , 'Prevalence' and 'India' in various combinations for selected drugs. Animal studies, case reports, clinical trials, non peer-reviewed publications, studies not in English and those with less than 100 participants were excluded. Additional studies were taken from Indian Pharmacopoeia Commission (IPC) reports and publications. Prospective and retrospective cohort studies, cross-sectional and case-control studies were included. Once the drug, sADR and prevalence in Indian patients were identified, at least 2 international studies were searched using similar methodology (excluding 'India' as a search term) for estimating the prevalence in other countries. If the prevalence of this sADR was comparable (less than 5% difference), it was excluded. Where multiple eligible studies existed, matching of study design and methodology was done between Indian and international literature and the study with the most robust reporting was preferred. Any discrepancies during study selection and data extraction were resolved through consensus and discussion among all authors. In addition, FDA Adverse Event Reporting System (FAERS) data was also extracted for each selected drug and sADR.
Statistical Analysis
Data was compiled in MS Excel sheet, and prevalence rates were compared between Indian and international studies to highlight the differences. The FAERS data was reported as Reporting Odds Ratio (ROR), which is a measure of disproportionality in pharmacovigilance used to identify potential drug-related adverse events. An ROR more than 1 indicates that the adverse event is reported more frequently in association with the target drug than expected, suggesting a potential safety signal.
RESULTS
Study selection
An initial PubMed search was conducted to identify the availability of Indian data as per inclusion criteria. Using combinations of keywords (Figure 1), 3265 Indian records were obtained. Additionally, 48 records were obtained using IPC reports and PvPI publications to further substantiate the selection of drugs and sADRs. Using 'FAERS' as a search term, relevant studies were also identified. Animal studies, case reports, clinical trials, letters, duplicates, and other articles that were not relevant were excluded. 27 studies were excluded on screening as per the inclusion criteria and comparison of search methodology. After final assessment and discussion, 22 studies including 10 drugs with their sADRs were included Figure 1, Table 1.
Study findings
The majority of Indian studies reported a higher prevalence of sADRs compared to global counterparts (Table 1). Ethambutol-induced optic neuropathy, for example, was reported in up to 14% of Indian patients, a striking contrast to the 2% prevalence observed among the patients in the United States. Linezolid-associated peripheral neuropathy was observed in 93.3% of Indian patients compared to just 1.6% in international studies. A similar trend was noted for nifedipine, a Calcium Channel Blocker (CCB) that led to gingival hypertrophy in 75% of Indian patients. The prevalence reported in patients in England was only 6.3%. NSAIDs (Non-Steroidal Anti-Inflammatory Drugs) resulted in renal complications in 27.88% of Indian patients, compared to 13% in American populations. In case of certain drugs, reported rates of ADRs were lower in India compared to other countries. For example, Lamivudine-induced hearing loss was lower in India at 3%, as opposed to 35.8% in a Brazilian cohort, and Pioglitazone was associated with bladder cancer in 2% of Indian patients compared to a significantly higher rate (53%) reported elsewhere. FAERS data (Table 2) was found for 6 drugs, all having ROR more than one. The lowest reported ROR (2.45) was that of NSAID-induced renal injury.
DISCUSSION
Our findings highlight marked differences in drug safety profiles and a higher prevalence of serious ADRs among Indian patients for many drugs.
Carbamazepine and Phenytoin have been implicated in drug-induced SJS and TEN in 18.25% (Agarwal et al., 2014) and 13.37% (Patel et al., 2013) of Indian patients, respectively, compared to significantly lower rates in European patients (Gidal, 2011; Rodríguez-Martín S et al., 2019). HLA-B1502 has been shown to present carbamazepine directly to cytotoxic T cells without prior antigen processing, triggering an immune response. National PvPI data indicate that 2% of suspected bladder cancer cases were due to Pioglitazone (Bhushan et al., 2019). In contrast, U.S. reports show 53% of pioglitazone-related individual case safety reports involving suspected bladder cancer. Authors postulate that differences in the genetic metabolism, cigarette smoking could influence this varied prevalence. An Indian study across 8 tertiary centres reported a prevalence of 27.88% for NSAID-induced renal complications (Chatterjee S et al., 2015). A study in the US population, with more than 12,000 participants, demonstrated 13% of patients developing Chronic Kidney Disease (CKD) with use of NSAIDs (Platinga L et al., 2011). NSAIDs-mediated inhibition of prostaglandin synthesis can impair renal blood flow, culminating in kidney injury. Gum hyperplasia induced by Nifedipine and Amlodipine was reported in 75% and 31.4% of Indian patients respectively (Gopal et al., 2015). These numbers were significantly higher than that reported in 6.3% and 1.7% of 911 patients in England (Prisant & Herman,
2002). CCBs downregulate connective tissue degradation with increased production of collagen by gingival fibroblasts.
Lamivudine can result in hearing loss. An Indian study reported that hearing loss was observed in 3% of the patients receiving Highly Active Antiretroviral Therapy (HAART) (Doseman D et al., 2018), compared to a Brazilian study where 35.8% of 106 patients complained of hearing loss (Silva et al., 2011). Lamivudine-induced mitochondrial dysfunction via polymerase gamma inhibition contributes to this adverse effect. Zidovudine causes anemia through bone marrow suppression and mitochondrial toxicity.
In India, the prevalence of zidovudine-induced anemia has been reported to be 14.6% (Dash KR et al., 2015), which is notably lower than the pooled global prevalence of 39.7% (Cal G et al., 2022). The prevalence of Ethambutol-induced optic neuropathy in India is reported to be 14% (Kumar SR et al., 2024), compared to 2% in the US population (Roussos & Tsolkas, 1970). High prevalence of Tuberculosis with extensive use of this drug could be contributory. Selective damage to the papillomacular bundle with mitochondrial dysfunction are important mechanisms. Linezolid can cause peripheral neuropathy and anemia due to ribosomal dysfunction. An Indian study reported that 93.33% patients developed peripheral neuropathy (Mishra et al., 2024) compared to a Belgian study with significantly low prevalence (Thirot et al., 2021), and the FAERS database with peripheral neuropathy in 36.04-46.37% (Zou et al., 2024).
We observed that while serious ADRs are reported in global pharmacovigilance systems, their prevalence is notably higher in Indian patients for most drugs. An analysis of the FAERS data (Borrelli et al., 2018; Hatahira et al., 2017; Piccinni et al., 2011; Shao et al, 2021; Zou et al., 2024) (Table 2) revealed that Indian prevalence rates were significantly higher than the corresponding ROR. Indian data show a 75% prevalence of gingival hyperplasia with Nifedipine, significantly higher than the 9.3 ROR in the FAERS database. Similarly, Linezolid-induced peripheral neuropathy exhibited a 93.33% prevalence in India compared to a relatively low ROR of 8.23 in FAERS. Drug induced serious ADRs could be manifested due to several reasons. Among the drugs examined, genetic predisposition is implicated in the adverse effects of carbamazepine, phenytoin and pioglitazone. In other cases, ADRs appeared to be extensions of the pharmacological action of the drug, as observed with NSAIDs, CCBs, lamivudine, zidovudine, linezolid, and ethambutol. This suggests the influence of genetic variability, environmental exposures, healthcare delivery standards, and pharmacovigilance infrastructure. The evidence strongly supports the need for more robust, localized pharmacovigilance systems in India to detect, report, and manage ADRs effectively, thereby ensuring safer medication practices tailored to Indian populations.
Table 1 Comparison of prevalence of ADRs of drugs in India and other countries.
| Drug | ADR | Prevalence (Indian studies) (n=9) (Cao et al., 2022; Chatterjee et al., 2015; Gidal, 2011; Gopal et al., 2015; Insani et al., 2021; Miguel et al., 2012; Patel et al., 2007; Piccinni et al., 2011; Prisant et al., 2002) | Prevalence (other countries) (n=8) (Dash et al., 2015; Dosemane et al., 2018; Gidal, 2011; Hatahira et al., 2017; Kumar et al., 2024; Mishra et al., 2024; Patel et al., 2013; Plantinga et al., 2011; Rodríguez-Martín et al., 2019) |
|---|---|---|---|
| Carbamazepine | Stevens Johnson Syndrome (SJS) | 18.25% | 1 to 6 per 10,000 patients exposed |
| Phenytoin | SJS and Toxic Epidermal Necrolysis (TEN) | 13.37% | 68.9 per 100,000 patients exposed |
| Pioglitazone | Bladder cancer | 2% | 53% |
| Zidovudine | Anemia | 14.% | 40.25% |
| NSAIDs | Nephrotoxicity- Renal injury, Chronic Kidney Disease (CKD) | 27.88% | 13% |
| Nifedipine | Gingival hyperplasia | 75% | 6.3% |
| Amlodipine | Gingival hyperplasia | 31.4% | 1.7% |
| Lamivudine | Hearing impairment | 3% | 35.8 |
| Ethambutol | Optic neuropathy | 6-14% | 2% |
| Linezolid | Peripheral neuropathy | 93.33% | 1.6% |
Table 2 Reporting Odds Ratio (ROR) of ADRs of drugs as per FAERS database.
| Drug | ADR | ROR in USA (FAERS database) (Roussos et al., 1970; Shao et al., 2021; Silva et al., 2011; Thirot et al., 2021; Zou et al., 2024) |
|---|---|---|
| Nifedipine | Gingival hyperplasia | 9.3 |
| Amlodipine | Gingival hyperplasia | 20.9 |
| Carbamazepine | Steven Johnson Syndrome (SJS) | 24.5 |
| Phenytoin | Agranulocytosis | 26.3 |
| Linezolid | Peripheral neuropathy | 8.23 |
| Pioglitazone | Bladder cancer | 4.3 |
| NSAIDs | Nephrotoxicity- Renal injury, Chronic Kidney Disease (CKD) | 2.45 |
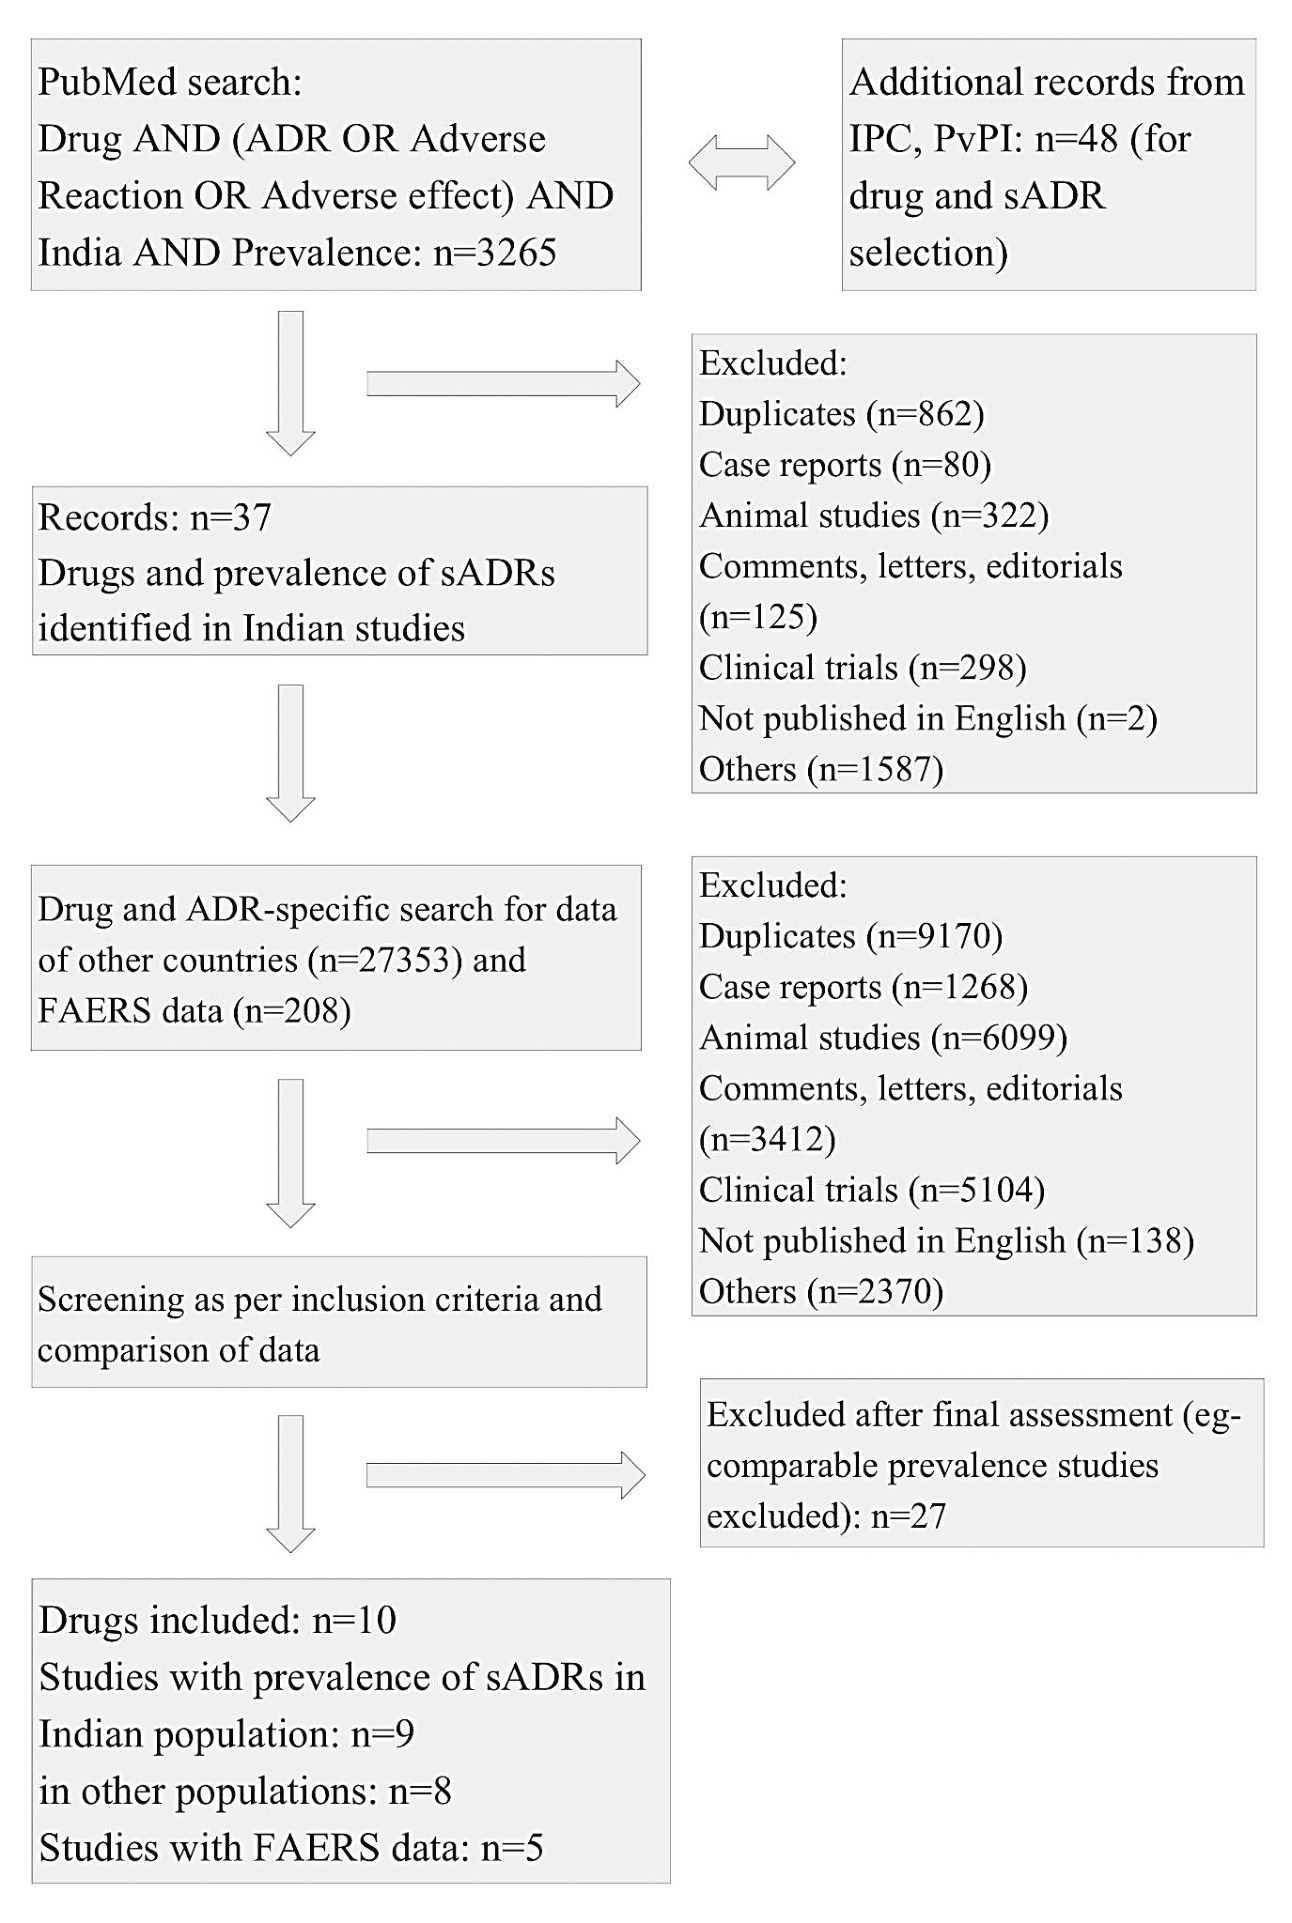
Figure 1
Study methodology: Selection of studies for comparison of prevalence of sADRs in Indian population and in other countries.
CONCLUSION
For the majority of the drugs evaluated, prevalence of sADRs was higher in the Indian population. A transparent and supportive reporting environment reinforced by policy incentives and public access to a comprehensive database is essential to understand the prevalence, etiology, and mechanisms for these observed differences of sADRs in the Indian population.
LIMITATIONS
This study focused on few drugs due to limited availability of comprehensive, quality Indian data. The studies varied in sample size, design, and methods of data collection, making generalisability difficult. We cannot exclude publication bias as ADRs that were serious were more likely to be reported and published.
Abbreviations
ADR: Adverse Drug Reaction
sADR: Serious Adverse Drug Reaction
PvPI: Pharmacovigilance Programme of India
IPC: Indian Pharmacopoeia Commission
FAERS: FDA Adverse Event Reporting System
ROR: Reporting Odds Ratio
CCB: Calcium Channel Blocker
NSAID: Non-Steroidal Anti-Inflammatory Drugs
CKD: Chronic Kidney Disease
HAART: Highly Active Antiretroviral Therapy
SJS: Stevens–Johnson Syndrome
TEN: Toxic Epidermal Necrolysis.
Author Contributions
Pravartika Gandhi and Ranveer Sahrawat conducted literature search and data extraction. Preeta Kaur Chugh conceptualized the study, resolved discrepancies, and finalized the manuscript. All authors read and approved the final manuscript.
Conflict of Interest
The authors declare that there is no conflict of interest.
References
Aggarwal, R., Sharma, M., Modi, M., Garg, V., Salaria, M.. (2014). HLA-B * 1502 is associated with carbamazepine induced Stevens-Johnson syndrome in North Indian population. Human Immunology, 75(11), 1120-2. https://doi.org/10.1016/j.humimm.2014.09.022
Bhushan, S., Ray, R., Prakash, J., Singh, G.. (2019). Global Versus Indian Perspective of Pioglitazone-induced Adverse Drug Reactions Including Bladder Cancer: A Comparative Retrospective Pharmacovigilance Analysis. Clinical Therapeutics, 41(11), 2252-62. https://doi.org/10.1016/j.clinthera.2019.08.018
Borrelli, E., Lee, E., Descoteaux, A., Kogut, S., Caffrey, A.. (2018). Stevens-Johnson syndrome and toxic epidermal necrolysis with antiepileptic drugs: An analysis of the US Food and Drug Administration Adverse Event Reporting System. Epilepsia, 59(12), 2318-24. https://doi.org/10.1111/epi.14591
Cao, G., Wang, Y., Wu, Y., Jing, W., Liu, J., Liu, M.. (2022). Prevalence of anemia among people living with HIV: A systematic review and meta-analysis. eClinicalMedicine, 44, 101283. https://doi.org/10.1016/j.eclinm.2022.101283
Chatterjee, S., Dureja, G., Kadhe, G., Mane, A., Phansalkar, A., Sawant, S., Kapatkar, V.. (2015). Cross-Sectional Study for Prevalence of Non-Steroidal Anti-Inflammatory Drug-Induced Gastrointestinal, Cardiac and Renal Complications in India: Interim Report. Gastroenterology Research, 8(3-4), 3-4. https://doi.org/10.14740/gr658w
Dash, K., Meher, L., Hui, P., Behera, S., Nayak, S.. (2014). High Incidence of Zidovudine Induced Anaemia in HIV Infected Patients in Southern Odisha. Indian Journal of Hematology and Blood Transfusion, 31(2), 247-50. https://doi.org/10.1007/s12288-014-0426-9
Dosemane, D., Kumar, V., Madi, D., Kanthila, J.. (2018). Human Immunodeficiency Virus Infection: Does Highly Active Antiretroviral Therapy Influence Ear Nose Throat Manifestations?. Indian Journal of Otolaryngology and Head & Neck Surgery, 70(4), 555-8. https://doi.org/10.1007/s12070-018-1420-6
Gidal, B.. (2011). Carbamazepine Hypersensitivity: Progress toward Predicting the Unpredictable. Epilepsy Currents, 11(6), 189-91. https://doi.org/10.5698/1535-7511-11.6.189
Gopal, S., Joseph, R., Santhosh, V., Kumar, V., Joseph, S., Shete, A.. (2015). Prevalence of gingival overgrowth induced by antihypertensive drugs: A hospital-based study. Journal of Indian Society of Periodontology, 19(3), 308-11. https://doi.org/10.4103/0972-124x.153483
Hatahira, H., Abe, J., Hane, Y., Matsui, T., Sasaoka, S., Motooka, Y., Hasegawa, S., Fukuda, A., Naganuma, M., Ohmori, T., Kinosada, Y., Nakamura, M.. (2017). Drug-induced gingival hyperplasia: A retrospective study using spontaneous reporting system databases. Journal of Pharmaceutical Health Care and Sciences, 3(1), 19. https://doi.org/10.1186/s40780-017-0088-5
Insani, W., Whittlesea, C., Alwafi, H., Man, K., Chapman, S., Wei, L.. (2021). Prevalence of adverse drug reactions in the primary care setting: A systematic review and meta-analysis. PLOS ONE, 16(5), e0252161. https://doi.org/10.1371/journal.pone.0252161
Kumar, S., Hissar, S., Ramesh, P., Shanmugam, M., Kalaiselvan, V., Prakash, J., Padmapriyadarsini, C.. (2024). Ethambutol-induced optic neuropathy: Should we mandate ophthalmic examination in TB treatment?. The International Journal of Tuberculosis and Lung Disease, 28(1), 51-3. https://doi.org/10.5588/ijtld.23.0304
Miguel, A., Azevedo, L., Araújo, M., Pereira, A.. (2012). Frequency of adverse drug reactions in hospitalized patients: A systematic review and meta-analysis. Pharmacoepidemiology and Drug Safety, 21(11), 1139-54. https://doi.org/10.1002/pds.3309
Mishra, G., Alffenaar, J., Munje, R., Khateeb, S.. (2024). Adverse drug reactions due to linezolid in the programmatic management of drug-resistant tuberculosis in India: A retrospective multicenter study. Indian Journal of Tuberculosis, 71, S101-S109. https://doi.org/10.1016/j.ijtb.2023.04.006
Patel, K., Kedia, M., Bajpai, D., Mehta, S., Kshirsagar, N., Gogtay, N.. (2007). Evaluation of the prevalence and economic burden of adverse drug reactions presenting to the medical emergency department of a tertiary referral centre: A prospective study. BMC Clinical Pharmacology, 7(1), 8. https://doi.org/10.1186/1472-6904-7-8
Patel, T., Barvaliya, M., Sharma, D., Tripathi, C.. (2013). A systematic review of the drug-induced Stevens-Johnson syndrome and toxic epidermal necrolysis in Indian population. Indian Journal of Dermatology, Venereology, and Leprology, 79(3), 389-98. https://doi.org/10.4103/0378-6323.110749
Piccinni, C., Motola, D., Marchesini, G., Poluzzi, E.. (2011). Assessing the Association of Pioglitazone Use and Bladder Cancer Through Drug Adverse Event Reporting. Diabetes Care, 34(6), 1369-71. https://doi.org/10.2337/dc10-2412
Plantinga, L., Grubbs, V., Sarkar, U., Hsu, C., Hedgeman, E., Robinson, B., Saran, R., Geiss, L., Burrows, N., Eberhardt, M., Powe, N.. (2011). Nonsteroidal Anti-Inflammatory Drug Use Among Persons With Chronic Kidney Disease in the United States. The Annals of Family Medicine, 9(5), 423-30. https://doi.org/10.1370/afm.1302
Prisant, L., Herman, W.. (2002). Calcium Channel Blocker Induced Gingival Overgrowth. The Journal of Clinical Hypertension, 4(4), 310-1. https://doi.org/10.1111/j.1524-6175.2002.01095.x
Rodríguez-Martín, S. M. E. L. V. R. A. G. O. G. C. R. E. B. T. A. D. &. F.. (2018). Incidence of Stevens-Johnson syndrome/toxic epidermal necrolysis among new users of different individual drugs in a European population: A case-population study. European Journal of Clinical Pharmacology, 75(2), 237-246. https://doi.org/10.1007/s00228-018-2569-3
Roussos, T., Ophthalmol., T. A. T. T. O. M. O. T. H. E. A.. (1970). ;2:578-80.
Shao, Q., Yin, X., Liu, H., Zhao, B., Huang, J., Li, Z.. (2021). Kidney Injury Following Ibuprofen and Acetaminophen: A Real-World Analysis of Post-Marketing Surveillance Data. Frontiers in Pharmacology, 12. https://doi.org/10.3389/fphar.2021.750108
Silva, A., Latorre, M., Tanaka, L., Oliveira, T., Mendes, E., Marques, H.. (2011). P2-281 Prevalence of hearing loss in HIV-infected Brazilian children and adolescents. Journal of Epidemiology and Community Health, 65(Suppl 1), A299. https://doi.org/10.1136/jech.2011.142976k.14
Thirot, H. B. C. F. F. J. F. H. X. H. S. T. P. S. A. B. V. &. F.. (2021). Clinical Use and Adverse Drug Reactions of Linezolid: A Retrospective Study in Four Belgian Hospital Centers. Antibiotics, 10(5), 530. https://doi.org/10.3390/antibiotics10050530
Zou, F., Cui, Z., Lou, S., Ou, Y., Zhu, C., Shu, C., Chen, J., Zhao, R., Wu, Z., Wang, L., Chen, Z., Chen, H., Lan, Y.. (2024). Adverse drug events associated with linezolid administration: A real-world pharmacovigilance study from 2004 to 2023 using the FAERS database. Frontiers in Pharmacology, 15. https://doi.org/10.3389/fphar.2024.1338902