


Background: Polycystic Ovary Syndrome (PCOS) is a common endocrine disorder among women of reproductive age. It is marked by hormonal imbalance, ovulatory dysfunction, and metabolic irregularities, which can contribute to infertility and long-term health risks.
Objectives: This study aimed to evaluate the clinical features and treatment practices in patients diagnosed with PCOS.
Materials and Methods: A retrospective observational analysis was carried out using medical records of 65 PCOS patients at a tertiary care Ayurvedic hospital. Data on demographics, menstrual history, clinical symptoms, and therapeutic interventions were collected. Descriptive statistics were applied, and findings were presented as frequencies and percentages.
Results: The majority of patients were aged 19-25 years (53.1%), followed by those aged 26-35 years (30.3%). Menstrual irregularities were reported in 90.8% of cases. The most frequent clinical manifestations included acne (93.8%), hair fall (89.2%), obesity (87.7%), and hirsutism (68%). Infertility was documented in 41.5% of patients. Regarding management, Panchakarma therapy was administered in 50.8% of cases, while 56.9% received oral medications.
Conclusion: PCOS primarily affects younger women and is strongly associated with menstrual disturbances and dermatological symptoms. The findings highlight that both Ayurvedic therapies and pharmacological treatments are commonly employed, reflecting an integrative approach to PCOS management.
Abstract
Share on Mobile
Scan to access on mobile
Keywords
Ayurvedic Treatment
Hyperandrogenism
Infertility
Insulin Resistance
Panchakarma
Polycystic Ovary Syndrome
INTRODUCTION
Polycystic Ovary Syndrome (PCOS) also known as the Stein-Leventhal syndrome, is a prevalent endocrine disorder affecting women of reproductive age (Azziz et al., 2009). This syndrome is a heterogeneous endocrine disorder characterized by enlarged and dysfunctional ovaries, excess androgen levels, resistance to insulin. The name comes from the observation of small follicles (or "cysts") that often appear on the ovaries (Fauser et al., 2012). According to the WHO, PCOS affects approximately 8%-13% of women in their reproductive years (World Health Organization, 2023). Multiple comorbidities that are associated with PCOS include infertility, metabolic syndrome, obesity, impaired glucose tolerance, type 2 diabetes mellitus, cardiovascular disease, depression, Obstructive Sleep Apnea (OSA), endometrial cancer, and Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD) (Escobar-Morreale, 2018). It is characterized by hyperandrogenism, ovulatory dysfunction, and polycystic ovarian morphology, often accompanied by insulin resistance, obesity, dyslipidemia, and infertility (Goodarzi et al., 2011). The cause of PCOS is unknown but women with a family history or type 2 diabetes are at higher risk. PCOS is diagnosed clinically when at least two of the feature are present: Irregular or absent ovulation, Clinical or biochemical signs of hyperandrogenism, Polycystic ovarian features on ultrasound (Diamanti et al., 2012).
Dysfunction-Associated Steatotic Liver Disease (MASLD) (Escobar-Morreale, 2018). It is characterized
Newer Pharmacological Agents in PCOS
Recently, several novel drugs have been studied for PCOS management: Inositols (myo-inositol and D-chiro-inositol) improve insulin sensitivity and ovulatory function by modulating intracellular signaling pathways associated with insulin resistance (Unfer et al., 2017; Bevilacqua et al., 2019). Glucagon-Like Peptide-1 Receptor Agonists (GLP1-RAs) such as Liraglutide have shown promise in weight reduction and metabolic improvement in PCOS patients, particularly in those with obesity and impaired glucose tolerance (Jensterle et al., 2015; Rasmussen and Lindenberg, 2014). Sodium-Glucose Co-Transporter-2 (SGLT2) inhibitors, e.g., Dapagliflozin, are under investigation for their role in reducing insulin resistance and visceral adiposity in PCOS, although their clinical use is still emerging (Javed et al., 2021; Elkind-Hirsch et al., 2018). Research indicates that SGLT-2 inhibitors may help reduce body weight, visceral adiposity, and androgen levels, thereby improving metabolic and reproductive outcomes in PCOS patients (Elkind et al., 2018). Dipeptidyl Peptidase-4 (DPP-4) Inhibitors such as sitagliptin and linagliptin enhance incretin hormone activity and improve glucose metabolism. These drugs may improve insulin sensitivity, beta-cell function, and metabolic parameters in women with PCOS (Papaetis et al., 2021).
Ayurvedic Perspective and Management
Ayurveda approaches PCOS through a holistic framework, focusing on restoring metabolic balance (Agni), hormonal regulation, and maintaining equilibrium of doshas, especially Kapha dosha (Mishra, 2004). Ayurvedic management generally includes herbal remedies, dietary modifications, and lifestyle practices.
Herbal Remedies
Herbs are the hidden gems of the plant world, used in Ayurveda for centuries.
Ashwagandha (Withania somnifera)
It helps in managing stress, which is a critical factor in hormonal imbalance and PCOS. These herbal remedies for PCOS support the endocrine system by balancing cortisol levels. Ashwagandha works like a natural mood booster for women with PCOS. It alleviates anxiety and irregular periods (Singh et al., 2011).
Shatavari (Asparagus racemosus)
Shatavari is one of the well-known Ayurvedic herbal remedies for PCOS. This herb promotes hormonal balance by modulating estrogen levels. It improves fertility and supports regular menstrual cycles. Shatavari's antioxidant and anti-inflammatory properties decrease PCOS-related symptoms. Thus, it promotes healthy reproductive health in women.
Turmeric (Curcuma longa)
Turmeric helps resolve chronic inflammation and insulin resistance associated with PCOS. It also improves metabolic function and modulates estrogenic activity in female reproductive organs. It can also ease symptoms like acne and weight gain (Gupta et al., 2013).
Lodhra (Symplocos racemosa)
It helps control excessive bleeding and correct hormonal imbalance (Tillu et al., 2015).
Ashoka (Saraca asoca)
It regulates menstrual cycles and improves uterine health (Singh, 2010).
Panchakarma for Infertility and PCOS
The "Panchakarma" therapy of Ayurveda provides a clear response to the rising problem of PCOS in the modern era. Therapy with panchakarma gives power to the sexual bodies such as the uterus, ovaries, Fallopian tubes, female vagina and male testis. The hormone equilibrium is preserved by panchakarma treatment.
Basti (Vasti)
For treatment with Basti, various types of herbal oils, Ghruta, milk or decoctions are used. Miracles may arise if they are treated correctly with suitable medications. Benefits of basti -Reduces Female Infertility = Irregular Menses, Hormone Unbalance, Dysmenorrhea, PCOD.
Uttarbasti
It seems to be the most effective therapy for gynecological conditions. Because of its resulting effects on the uterus and ovaries, it dissolves the cyst in the ovaries more efficiently than oral medications.
Dietary Recommendations
A PCOS diet chart to balance Kapha dosha includes some light, warm, and easy to digest food, including; Vegetables: Incorporate fresh vegetables into your diet. These may include leafy greens, broccoli, cauliflower, carrots, beets, and asparagus. Whole grains: Add whole grains such as brown rice, quinoa, and barley. Fruits: Avoid extra sweet or ripe fruit. Instead, have fruits like apples, berries, and pomegranate. Dry Fruits: It may include almonds, walnuts, pistachios, chia seeds, flax seeds, and berries. Legumes: Include legumes like lentils, chickpeas, and mung beans (Lad, 1999) (Tables 1 2 3 4).
Yoga and Exercise
Regular physical activity of minimum 30 min can be an effective solution for managing PCOS.
• Butterfly pose: Baddha Konasana, or Butterfly pose, is ideal for improving blood flow to the pelvic region.
• Cobra Pose: Bhujangasana or Cobra pose strengthens the back and stretches the chest. This improves posture and relieves stress. This pose helps regulate the adrenal gland, balancing cortisol levels.
• Pranayama (Breathing Exercises): It supports the menstrual cycle in PCOS management (Healthline, n.d.) (Katore and Bhingare, 2024).
Pathophysiology of PCOS
PCOS is a multifactorial endocrine and metabolic disorder affecting women of reproductive age. Its mechanism involves hormonal imbalance, insulin resistance, genetic predisposition, and ovarian dysfunction, which together lead to the characteristic symptoms such as irregular menstruation, hyperandrogenism, and polycystic ovaries.
Hypothalamic-Pituitary-Ovarian (HPO) Axis Dysfunction
The hypothalamic-pituitary-ovarian axis regulates reproductive hormones. In PCOS, this axis becomes dysregulated. Mechanism: The hypothalamus secretes Gonadotropin-Releasing Hormone (GnRH) in increased pulse frequency. This stimulates the pituitary gland to produce more Luteinizing Hormone (LH) than Follicle-Stimulating Hormone (FSH). The LH/FSH ratio becomes elevated (often>2:1). High LH stimulates ovarian theca cells to produce excessive Androgens such as testosterone. Reduced FSH leads to impaired follicular maturation, preventing normal ovulation (Franks, 1995). Result: Chronic anovulation and accumulation of immature follicles in the ovaries (polycystic appearance) (Dumesic et al., 2015).
Insulin Resistance and Hyperinsulinemia
One of the most important mechanisms of PCOS is insulin resistance. Mechanism: Body cells become less sensitive to Insulin.The pancreas compensates by producing excess insulin (hyperinsulinemia). High insulin levels: Stimulate ovarian theca cells to produce more androgens. Reduce hepatic production of Sex Hormone Binding Globulin (SHBG) (Dunaif, 1997). Result: Increased free testosterone levels, worsening hyperandrogenism and symptoms like acne, hirsutism, and irregular menstruation (Ehrmann, 2005).
Hyperandrogenism
PCOS is characterized by excess androgen production from ovaries and adrenal glands. Mechanism: Increased LH and insulin stimulate ovarian theca cells. These cells produce high levels of testosterone and androstenedione. Reduced SHBG increases the biologically active form of testosterone. Effects: Hirsutism (excess hair growth), Acne, Alopecia, Disruption of normal follicular development (Azziz, 2005).
Ovarian Follicular Arrest
In PCOS, follicles start developing but fail to mature. Mechanism: 1. Low FSH levels prevent normal follicle maturation. 2. High androgen levels inhibit granulosa cell function. 3. Follicles remain in immature stages (2-9 mm size). Result: Multiple small follicles accumulate in ovaries and ovaries appear enlarged and polycystic on ultrasound (Rotterdam ESHRE/ASRM-Sponsored PCOS Consensus Workshop Group, 2004).
Genetic and Environmental Factors
PCOS also has a genetic predisposition. -Family history increases risk, Several genes affecting insulin signalling and androgen synthesis are involved. Environmental factors include: Obesity, Sedentary lifestyle, High-calorie diet. These factors worsen insulin resistance and hormonal imbalance (Barber et al., 2019).
Chronic Low-Grade Inflammation
Many PCOS patients exhibit low-grade inflammation. Mechanism: Increased inflammatory markers such as C-Reactive Protein (CRP) and inflammation, contribute to insulin resistance and ovarian dysfunction (González, 2012).
Conventional Management of PCOS
Management of PCOS focuses on symptom control, prevention of metabolic complications, and improvement of fertility outcomes (Teede et al., 2018).
Lifestyle Modifications
are the primary and most effective management approach for PCOS treatment.
Dietary changes
Balanced diet focusing on reduced calories, low glycemic index foods, and improved nutrient quality. Exercise and physical activity-Regular physical activity improves insulin sensitivity, supports weight reduction, and helps regulate menstrual cycles. Weight management-Even modest weight loss (~5% of body weight) is associated with significant clinical improvements in ovulation, hormonal balance, and metabolic markers (Moran et al., 2013).
Pharmacologic (Medication-Based) Management
When lifestyle measures alone are insufficient, medications are used based on specific symptoms. Hormonal contraceptives: The first-line treatment for women with symptomatic PCOS, specifically for issues such as menstrual irregularities, hirsutism, and acne, is a combined hormonal contraceptive (Legro et al., 2013). Anti-Androgen Therapy: Used when hyperandrogenic symptoms persist despite COCP (Combined Oral Contraceptive Pills) therapy. Spironolactone and Cyproterone acetate are common agents (Carmina and Lobo, 2006). Insulin-Sensitizing Agents: Metformin is the most widely used insulin-sensitizing drug in PCOS (González, 2012). Infertility Treatment: The first-line therapy for infertility in PCOS patients is Letrozole.
Psychosocial management
PCOS is strongly associated with reproductive and metabolic implications affecting patients' psychological functioning and satisfaction with life. Depression: In patients with PCOS evaluated with depression and/ or anxiety, psychological counseling by an appropriate professional is suggested, based on severity of disease.
Cardiovascular Risk Management
Specialist CV monitoring and care is recommended in all patients showing CV risk factors, irrespective of the severity of their symptoms.
MATERIALS AND METHODS
It is a retrospective, observational, record-based study. The study is conducted at the the Govindbhai Jorabhai Patel Ayurveda College, New V.V. Nagar. The study is carried out over a period of one-two months. Female patients who are diagnosed with PCOS. A total of approximately 50-100 patient medical records are included in the study.
Inclusion Criteria and exclusion criteria
Age group
Female patients aged 15-45 years. Patients whose medical records contained complete clinical data, including: Demographic details, Clinical symptoms, Laboratory investigations, Prescribed treatment patterns. Patients who received pharmacological or ayurvedic treatment for PCOS, such as: Hormonal therapy, Panchakarma treatment/Herbal medicament, Lifestyle modification therapy. Patients with documented clinical symptoms of PCOS, such as: Irregular menstruation, Hirsutism, Acne, Infertility, Obesity. The following patient records were excluded from the study: Female patients without a confirmed diagnosis of PCOS. Patients with incomplete or missing medical records, including lack of information on: Clinical profile, Diagnostic reports, Treatment details. Patients diagnosed with other endocrine disorders that may mimic PCOS symptoms, such as: Cushing Syndrome, Congenital Adrenal Hyperplasia, Hyperprolactinemia, Thyroid Disorders. Pregnant women diagnosed with PCOS during pregnancy. Patients undergoing treatment for other gynecological conditions unrelated to PCOS. Patients taking metformin are excluded.
Data Collection
Data were entered into Microsoft Excel and analyzed using basic descriptive statistics. Results are expressed as frequencies and percentages. No inferential statistical tests are applied as the study is observational and descriptive in nature. Data were obtained from hospital records /case sheets via google form. Variables include: Age, Body Mass Index (BMI), Menstrual history, Clinical features (hirsutism, cne), Biochemical and hormonal parameters (LH, FSH). Descriptive statistical methods were used to summarize patient characteristics. Categorical variables were expressed as frequencies and percentages. Data Presentation: The results were presented in Tables (age distribution, clinical features, treatment patterns) and Simple bar charts or pie charts (optional, for better visualization). No inferential statistical tests (such as t-test, chi-square test, p-values) were applied. This is because the study is observational, retrospective, and descriptive, with no comparison groups or interventions.
Level of Significance
Not applicable, as no hypothesis testing is performed.
Interpretation of Results
Interpretation were focused on describing trends and characteristics of PCOS in the study population.
Ethical Considerations
An approval was taken from the Institutional Ethics Committee of Govindbhai Jorabhai Patel Ayurveda College, New Vallabh Vidhyanagar and confidentiality of patient data was strictly maintained. (Approval No. CVMU/GJPIASR/ IEC/13/2026-27/82).
RESULTS
Among 65 patients diagnosed with PCOS, the majority belonged to the 19-25-year age group (53.1%), followed by 26-35 years (30.3%). Patients aged 12-18 years and 36-50 years constituted 12.5% and 6.3%, respectively (Figure 1). Irregular menstruation was observed in 90.8% of patients, whereas only 9.2% reported regular menstrual cycles (Figures 2 and 3).
Acne was the most common clinical manifestation (93.8%), followed by hair fall (89.2%), obesity (87.7%), hirsutism (68%), and infertility (41.5%) (Figure 4).
Panchakarma therapy was administered to 50.8% of patients, while 56.9% received oral Ayurvedic medications (Figure 5). Among 65 patients diagnosed with PCOS, the majority belonged to the 19-25-year age group (53.1%), followed by 26-35 years (30.3%). Patients aged 12-18 years and 36-50 years constituted 12.5% and 6.3%, respectively. (Figure 1). Irregular menstruation was observed in 90.8% of patients, whereas only 9.2% reported regular menstrual cycles. (Figures 2 and 3).
Acne was the most common clinical manifestation (93.8%), followed by hair fall (89.2%), obesity (87.7%), hirsutism (68%), and infertility (41.5%).
Panchakarma therapy was administered to 50.8% of patients, while 56.9% received oral Ayurvedic medications.
DISCUSSION
A total of 65 patients diagnosed with Polycystic Ovary Syndrome (PCOS) were included in this study. Among the study population, the majority of patients were in the 19-25 years age group (53.1%), followed by 26-35 years (30.3%). A smaller proportion of patients belonged to the 12-18 years group (12.5%), while the 36-50 years group accounted for 6.3% of the total participants. This indicates that PCOS was most prevalent among young adult women. Regarding menstrual cycle patterns, most of the patients had irregular menstrual cycles (90.8%), whereas only 9.2% of patients reported having a regular menstrual cycle. This highlights that menstrual irregularity is a common clinical feature among PCOS patients. Several clinical manifestations associated with PCOS were observed among the patients. Hirsutism was present in 68% of patients, while 32% did not show this condition. Acne was observed in 93.8% of patients, whereas 6.2% did not have acne. Infertility was reported in 41.5% of patients, while 58.5% did not report infertility. Hair fall was seen in 89.2% of patients, whereas 10.8% did not experience hair fall. Obesity was present in 87.7% of patients, while 12.3% were not obese. These findings indicate that acne, hair fall, and obesity were among the most common clinical features observed in the study population. In terms of treatment approaches, 50.8% of patients received Panchakarma therapy, while 49.2% did not undergo Panchakarma treatment. Additionally, 56.9% of patients were treated with oral medications, whereas 43.1% did not receive oral pharmacological therapy.
Overall, the results suggest that PCOS was most commonly observed among young women aged 19-25 years, with irregular menstruation, acne, hair fall, and obesity being the most prevalent clinical manifestations. Both Ayurvedic therapies and oral medications were commonly used in the management of PCOS patients.
Study Limitations
The present study has certain limitations that should be considered while interpreting the findings. First, the study was conducted at a single tertiary-care Ayurvedic hospital, which may limit the generalizability of the results to other healthcare settings and populations. Second, the retrospective observational design relied on existing medical records, making the study susceptible to incomplete documentation and information bias. Third, the relatively small sample size (N=65) may have limited the ability to identify less common clinical manifestations and treatment patterns. Additionally, detailed hormonal, biochemical, and metabolic parameters were not consistently available in all patient records; therefore, subgroup analyses based on endocrine and metabolic profiles could not be performed. Despite these limitations, the study provides valuable insights into the clinical characteristics and treatment practices among women with PCOS in an Ayurvedic healthcare setting and may serve as a foundation for future large-scale prospective studies.
Table 1 Shows the demographic details.
| Demographic Details Age (years) | Number of Patients (n=65) | Percentage of patients |
|---|---|---|
| 12 to 18 | 8 | 12.50% |
| 19 to 25 | 34 | 53.10% |
| 26 to 35 | 20 | 30.30% |
| 36 to 50 | 4 | 6.30% |
Table 2 Shows the menstrual patterns in girls and women included in the study.
| Menstrual History (Menstrual Cycle Pattern) | Number of Patients (n=65) | Percentage of patients |
|---|---|---|
| Regular | 6 | 9.20% |
| Irregular | 59 | 90.80% |
Table 3 Shows the Clinical features like hirsutism, acne, infertility, hairfall and obesity parameters.
| Clinical Features | Number of Patients (n=65) | Percentage of Patients |
|---|---|---|
| Hirsutism | 44 | 68 |
| Acne | 61 | 93.8 |
| Infertility | 27 | 41.5 |
| Hair fall | 58 | 89.2 |
| Obesity | 57 | 87.7 |
Table 4 Shows the Ayurvedic treatment like Panchakarma and Ayurvedic oral medications.
| Ayurvedic Treatment | Number of Patients (n=65) | Percentage of Patients |
|---|---|---|
| Panchakarma | 33 | 50.80% |
| Oral Medication | 37 | 56.90% |
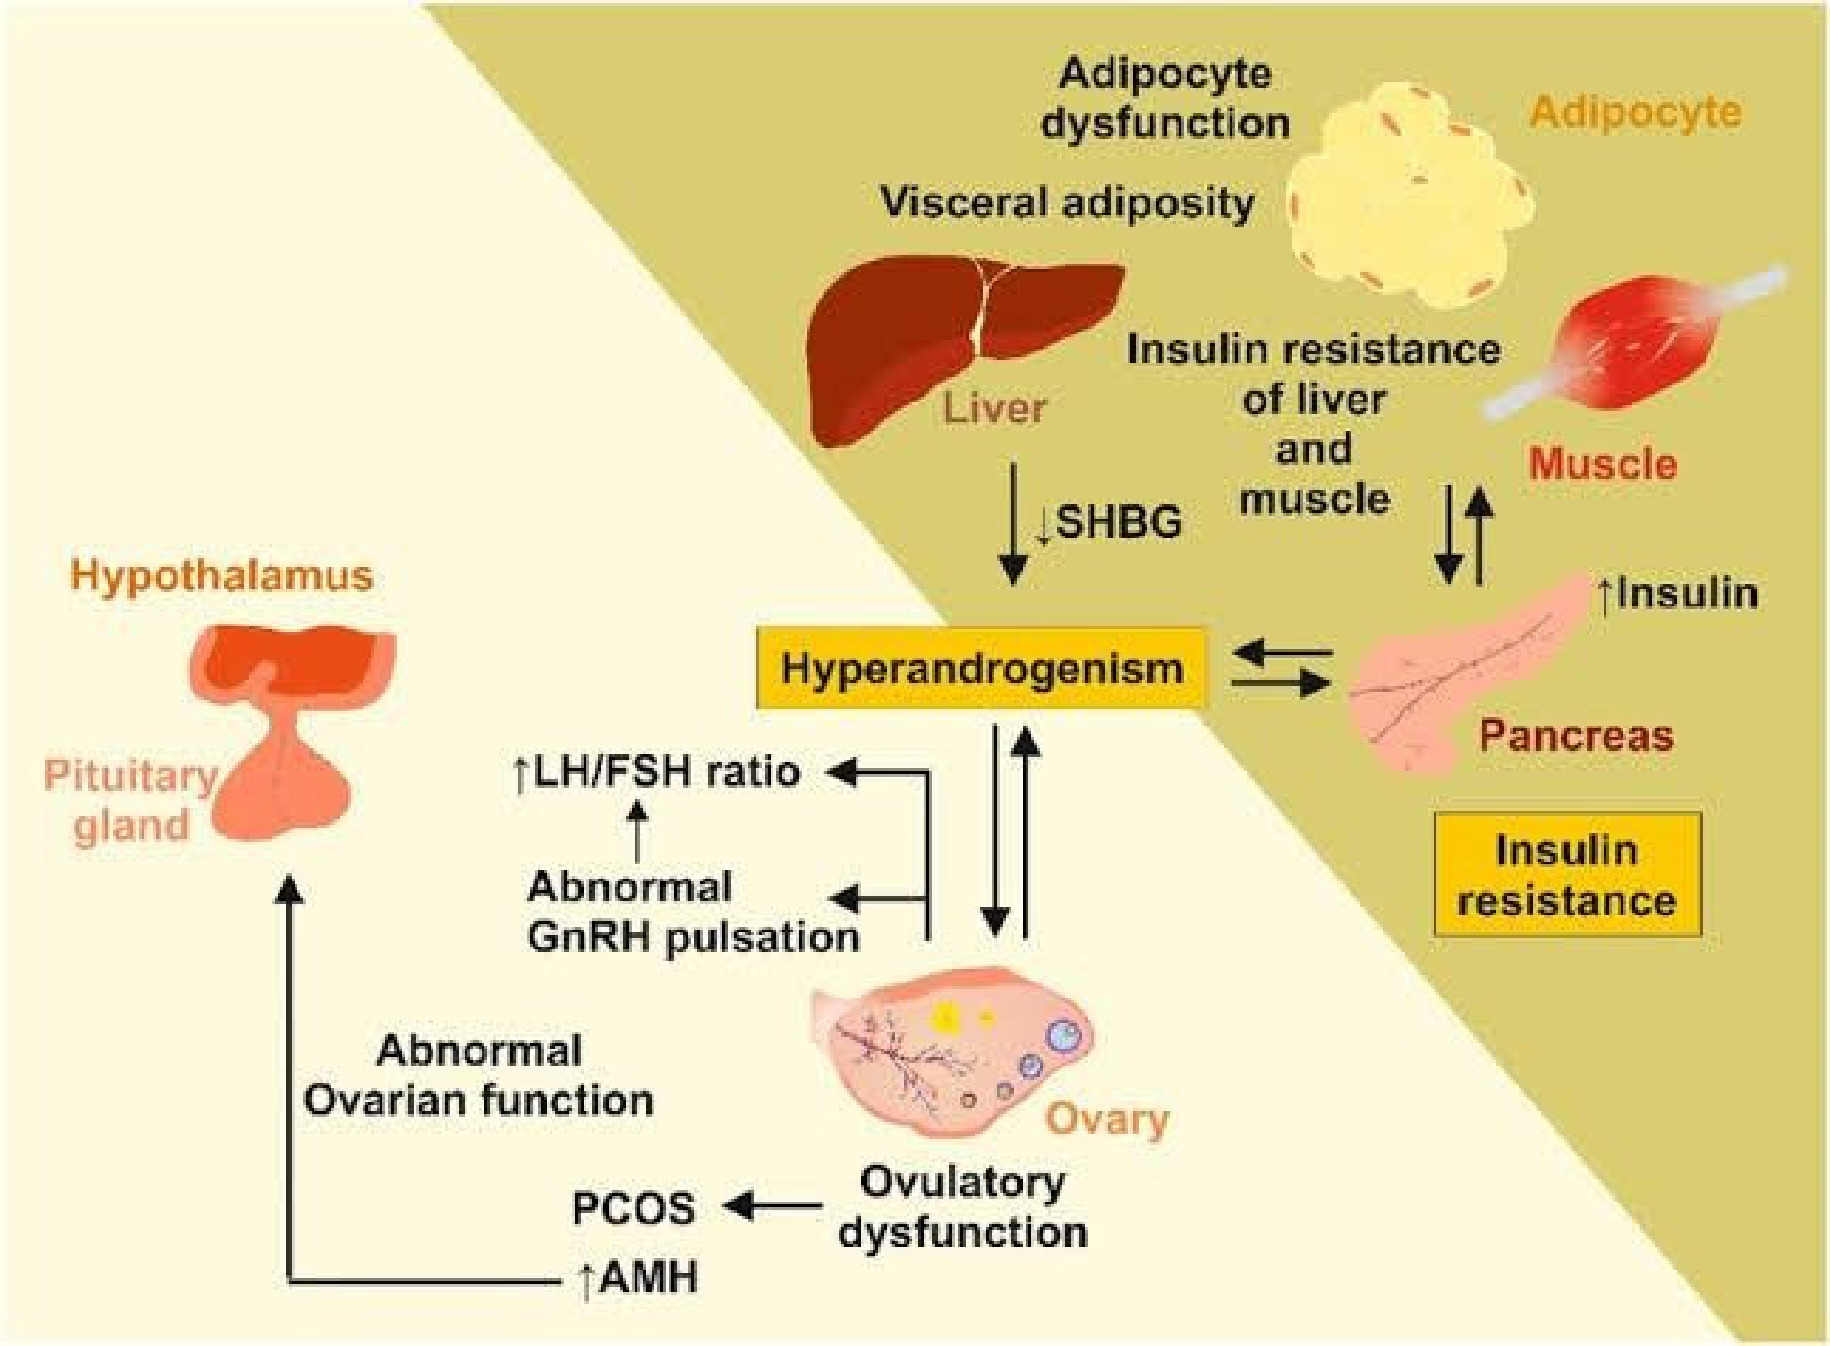
Figure 1
Pathophysiology of PCOS.
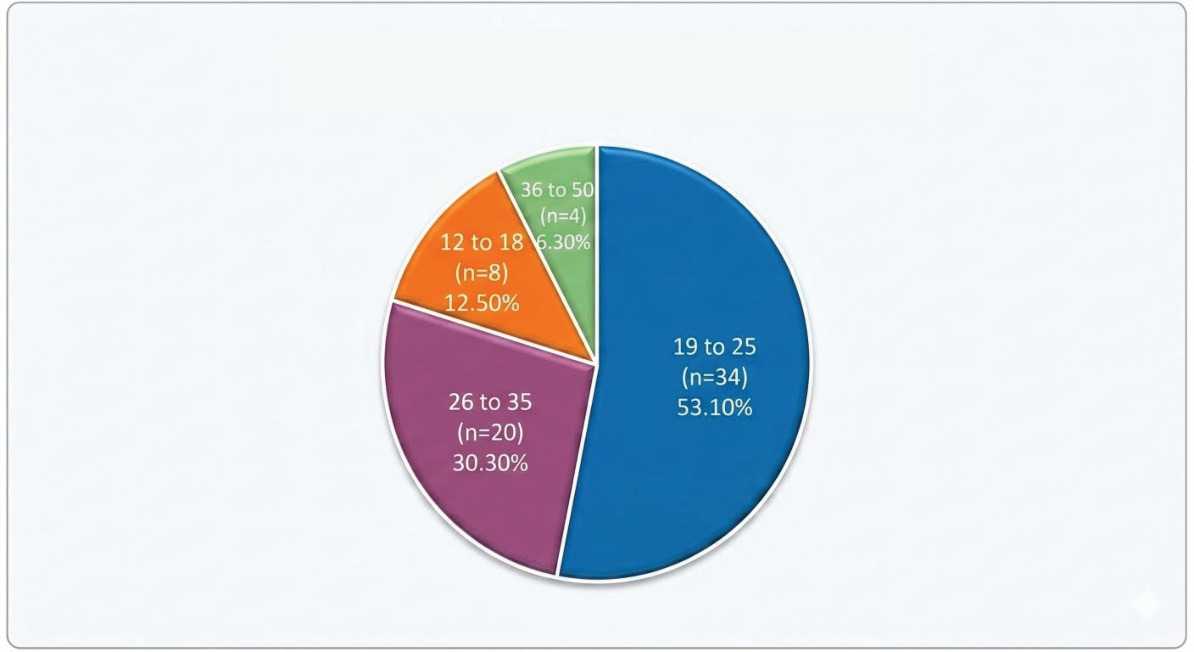
Figure 2
Graph showing the age of the Patients.
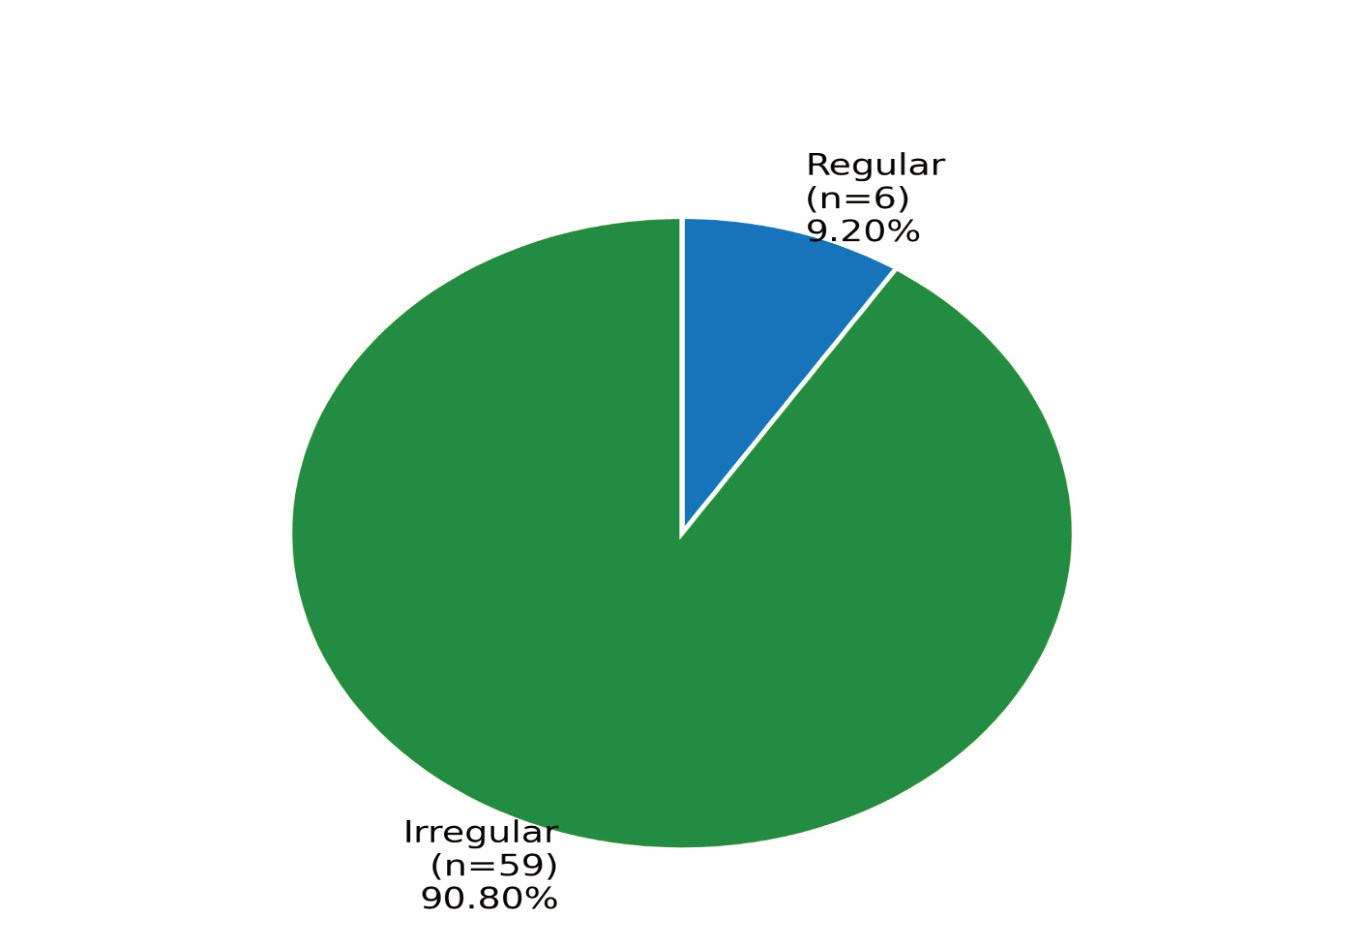
Figure 3
Graph showing the menstrual cycle pattern (n=65).
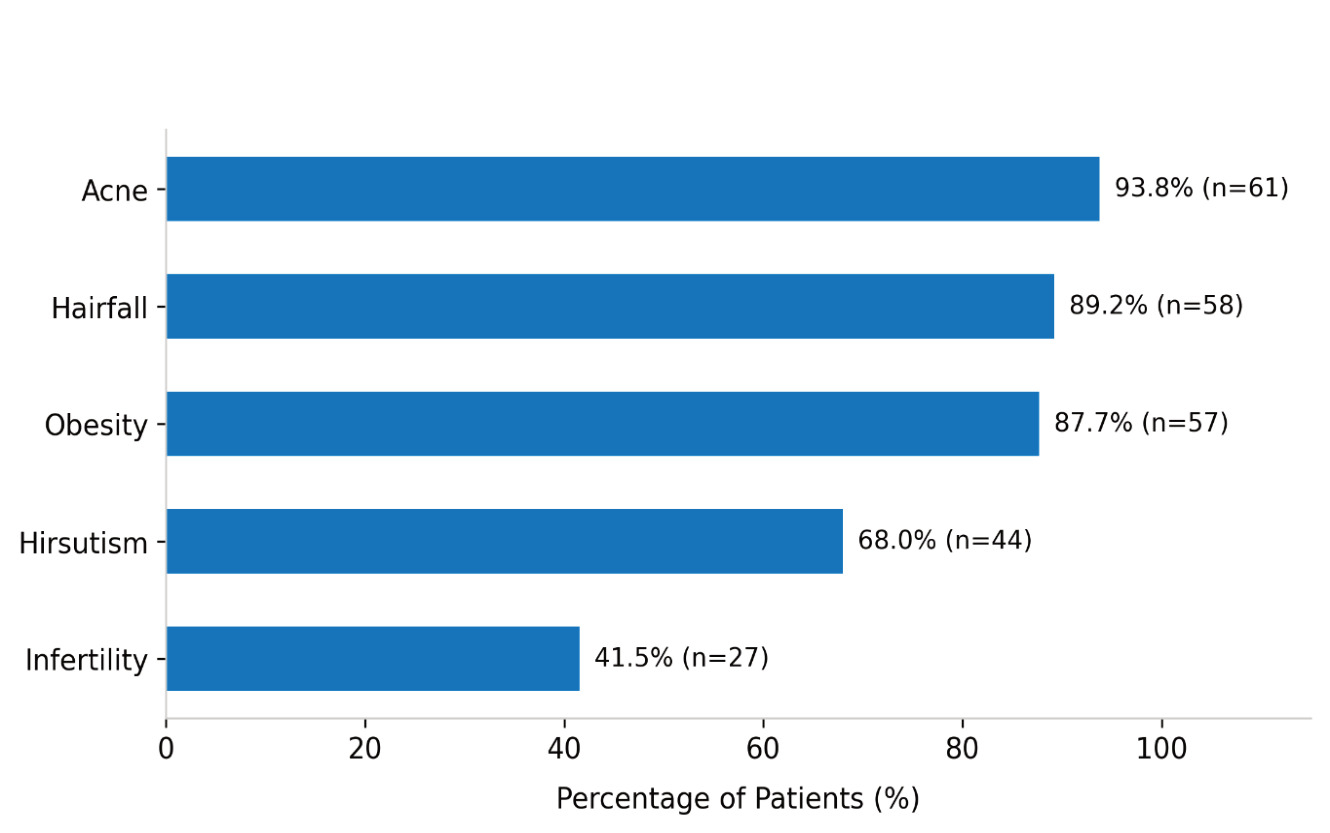
Figure 4
Graph showing the clinical features.
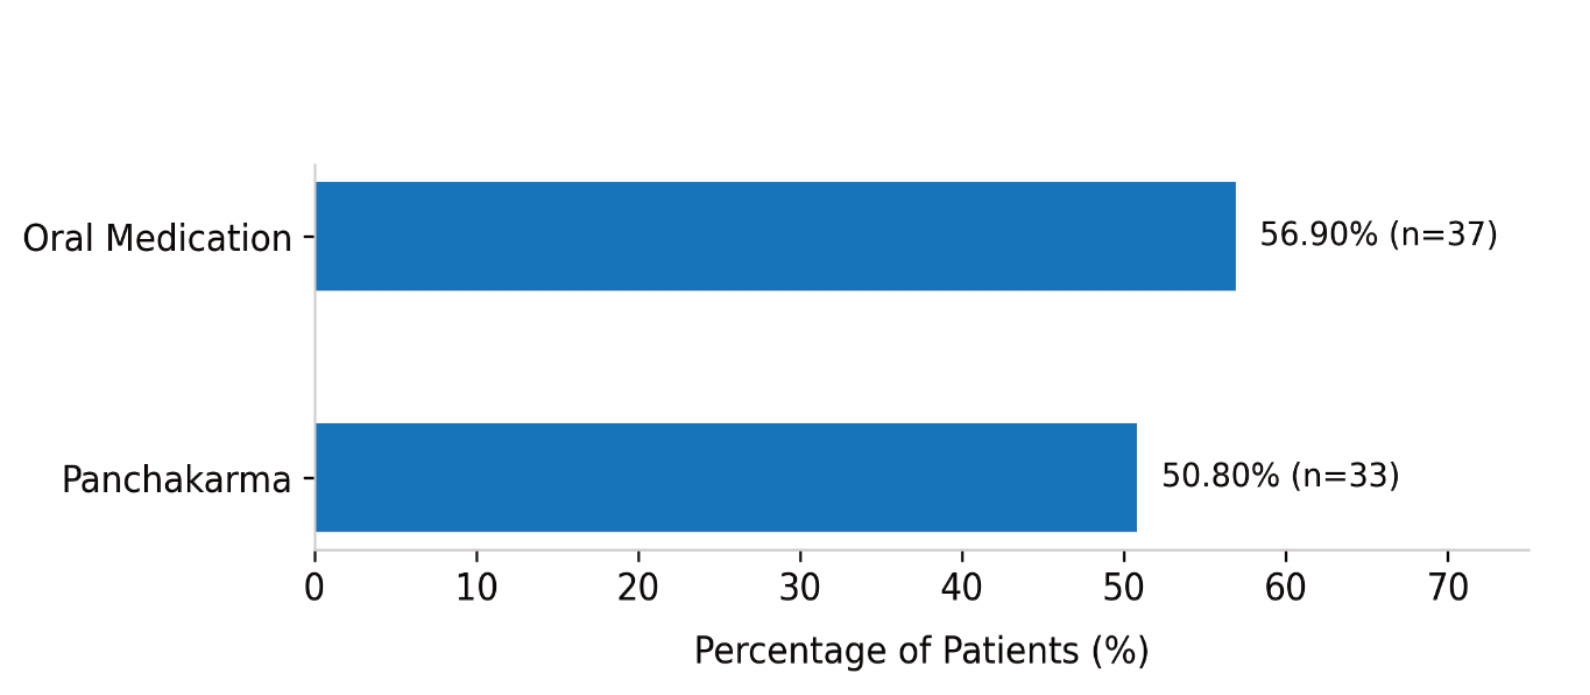
Figure 5
Graph showing ayurvedic treatment.
FUTURE DIRECTIONS
Future multicentric studies involving larger sample sizes and comparative treatment arms are needed to establish the long-term effectiveness of Ayurvedic interventions in PCOS management.
Randomized controlled studies comparing Ayurvedic and conventional pharmacological therapies may further strengthen evidence-based integrative management approaches.
CONCLUSION
This retrospective observational study provides valuable insights into the clinical profile and treatment patterns of women diagnosed with Polycystic Ovary Syndrome (PCOS). The findings highlight that PCOS is most prevalent among women in their reproductive years, particularly between 20-30 years of age, underscoring its impact on fertility and long-term health. Menstrual irregularities emerged as the most common clinical manifestation, while hirsutism, acne, obesity, and infertility were frequent associated features. These results reaffirm the heterogeneous nature of PCOS, which encompasses reproductive, metabolic, and psychological dimensions.
The treatment analysis revealed a strong reliance on Ayurvedic therapies and lifestyle modifications, reflecting the institutional setting of the study. Herbal remedies, Panchakarma therapies, dietary interventions, and yoga were widely prescribed, while pharmacological agents were used less frequently due to exclusion criteria. This integrated approach emphasizes the growing interest in complementary and alternative medicine for managing PCOS, particularly in regions where traditional practices are culturally embedded. Lifestyle interventions, including weight management and exercise, were consistently recommended, aligning with global guidelines that recognize lifestyle modification as the cornerstone of PCOS management.
Overall, the study underscores the importance of early diagnosis and individualized treatment strategies that combine lifestyle, pharmacological, and traditional approaches. By addressing both metabolic and reproductive aspects, such integrated management can improve clinical outcomes and enhance the quality of life of affected women. Future research should focus on larger, multi-centric studies with comparative designs to evaluate the long-term efficacy of Ayurvedic therapies alongside conventional pharmacological treatments. This will help establish evidence-based guidelines for holistic PCOS management and contribute to bridging the gap between modern medicine and traditional practices.
Abbreviations
PCOS: Polycystic Ovary Syndrome
WHO: World Health Organization
HPO: Hypothalamic-Pituitary-Ovarian
GnRH: Gonadotropin-Releasing Hormone
LH: Luteinizing Hormone
FSH: Follicle Stimulating Hormone
SHBG: Sex Hormone Binding Globulin
CRP: C-Reactive Protein
BMI: Body Mass Index
COCP: Combined Oral Contraceptive Pills
GLP-1 RA: Glucagon-Like Peptide-1 Receptor Agonist
SGLT2: Sodium-Glucose Co-Transporter 2
DPP-4: Dipeptidyl Peptidase 4
OSA: Obstructive Sleep Apnea
MASLD: Metabolic Dysfunction-Associated Steatotic Liver Disease.
Acknowledgments
The authors would like to acknowledge the support of the Indukaka Ipcowala College of Pharmacy, New V.V. Nagar, and the Govindbhai Jorabhai Patel Ayurveda College, New Vallabh Vidhyanagar for providing access to patient records and institutional facilities. We also extend our gratitude to the Institutional Ethics Committee for their guidance and approval, and to all healthcare professionals involved in patient care whose contributions made this study possible.
Author Contributions
Dudhat Himani Rameshbhai: Data collection, literature review, data analysis, and manuscript drafting. Yadav Khushi Umeshbhai: Data collection, literature review, and manuscript preparation. Patel Payal Rajeshbhai: Data collection, data analysis, and manuscript preparation. Dabhi Sherin Sandeepkumar: Data collection, literature review, and manuscript preparation. Mrs. Palak K. Vyas: Conceptualization, study design, supervision, manuscript review, editing, and final approval of the manuscript. All authors read and approved the final manuscript.
Conflict of Interest
The authors declare that there is no conflict of interest.
References
Azziz, R.. (2005). Androgen excess is the key element in polycystic ovary syndrome. Journal of Clinical Endocrinology & Metabolism, 90(5), 3106-3109. https://doi.org/10.1201/9780203910948.ch7
Azziz, R., Carmina, E., Dewailly, D., Diamanti-Kandarakis, E., Escobar-Morreale, H. F., Futterweit, W., et al.. (2009). The androgen excess and PCOS society criteria for the polycystic ovary syndrome: The complete task force report. Endocrine Reviews, 30(5), 467-520. https://doi.org/10.1016/j.fertnstert.2008.06.035
Azziz, R., Woods, K. S., Reyna, R., Key, T. J., Knochenhauer, E. S., Yildiz, B. O.. (2004). Prevalence and features of PCOS. Journal of Clinical Endocrinology & Metabolism, 89(6), 2745-2749. https://doi.org/10.1210/jc.2003-032046
Arentz, S., Smith, C. A., Abbott, J. A., Bensoussan, A.. (2017). Nutritional supplements and herbal medicines for PCOS. BMC Complementary and Alternative Medicine, 17, 1-10. https://doi.org/10.1186/s12906-017-2011-x
Banaszewska, B., Pawelczyk, L., Spaczynski, R. Z., Duleba, A. J.. (2011). Effects of simvastatin and metformin in PCOS. Journal of Clinical Endocrinology & Metabolism, 96(11), 3493-3501. https://doi.org/10.1210/jc.2011-0501
Barber, T. M., Franks, S., McCarthy, M. I.. (2019). Genetics of polycystic ovary syndrome. Nature Reviews Endocrinology, 15(6), 343-354. https://doi.org/10.1111/j.1365-2265.2006.02587.x
Bevilacqua, A., Carlomagno, G., Gerli, S., Montanino-Oliva, M., Unfer, V.. (2019). Myo-inositol and D-chiro-inositol in PCOS management. Gynecological Endocrinology, 35(2), 72-75. https://doi.org/10.3109/09513590.2015.1006616
Bozdag, G., Mumusoglu, S., Zengin, D., Karabulut, E., Yildiz, B. O.. (2016). Prevalence and phenotypic features of PCOS: A systematic review. Human Reproduction, 31(12), 2841-2855. https://doi.org/10.1093/humrep/dew218
Carmina, E., Lobo, R. A.. (2006). Treatment of hyperandrogenic alopecia and hirsutism in PCOS. Fertility and Sterility, 86(1), S45-S47. https://doi.org/10.1016/s0015-0282(02)04551-x
Diamanti-Kandarakis, E., Dunaif, A.. (2012). Insulin resistance and the polycystic ovary syndrome revisited: An update. Endocrine Reviews, 33(6), 981-1030. https://doi.org/10.1210/er.2011-1034
Dumesic, D. A., Oberfield, S. E., Stener-Victorin, E., Marshall, J. C., Laven, J. S., Legro, R. S.. (2015). Scientific statement on the diagnostic criteria, epidemiology and pathophysiology of PCOS. Endocrine Reviews, 36(5), 487-525. https://doi.org/10.1210/er.2015-1018
Dunaif, A.. (1997). Insulin resistance and the polycystic ovary syndrome: Mechanism and implications for pathogenesis. Endocrine Reviews, 18(6), 774-800. https://doi.org/10.1210/er.18.6.774
Ehrmann, D. A.. (2005). Polycystic ovary syndrome. New England Journal of Medicine, 352(12), 1223-1236. https://doi.org/10.1056/nejmra041536
Elkind-Hirsch, K., Chappell, N., Seidemann, E., Storment, J., Bellanger, D.. (2018). Use of SGLT-2 inhibitors in women with PCOS. Endocrine Practice, 24(7), 575-582. https://doi.org/10.21203/rs.3.rs-799341/v1
Escobar-Morreale, H. F.. (2018). Polycystic ovary syndrome: Definition, aetiology, diagnosis and treatment. Nature Reviews Endocrinology, 14(5), 270-284. https://doi.org/10.1038/nrendo.2018.24
Fauser, B. C. J. M., Tarlatzis, B. C., Rebar, R. W., Legro, R. S., Balen, A. H., Lobo, R., et al.. (2012). Consensus on women's health aspects of polycystic ovary syndrome. Human Reproduction Update, 18(5), 552-563. https://doi.org/10.1093/humrep/der396
Franks, S.. (1995). Polycystic ovary syndrome. New England Journal of Medicine, 333(13), 853-861. https://doi.org/10.1056/nejm199509283331307
Gambineri, A., Pelusi, C., Vicennati, V., Pagotto, U., Pasquali, R.. (2002). Obesity and PCOS. International Journal of Obesity, 26(7), 883-896. https://doi.org/10.1038/sj.ijo.0801994
Glueck, C. J., Goldenberg, N.. (2019). Characteristics of obesity in PCOS. Clinical Medicine Insights: Reproductive Health, 13, 1-8.
González, F.. (2012). Inflammation in polycystic ovary syndrome: Underpinning of insulin resistance and ovarian dysfunction. Fertility and Sterility, 97(2), 300-305. https://doi.org/10.1016/j.steroids.2011.12.003
Goodarzi, M. O., Dumesic, D. A., Chazenbalk, G., Azziz, R.. (2011). Polycystic ovary syndrome: Etiology, pathogenesis and diagnosis. Endocrine Reviews, 32(2), 168-193. https://doi.org/10.1038/nrendo.2010.217
Grant, P.. (2010). Spearmint herbal tea has anti-androgen effects in PCOS. Phytotherapy Research, 24(2), 186-188. https://doi.org/10.1002/ptr.2900
Gupta, S. C., Patchva, S., Aggarwal, B. B.. (2013). Therapeutic roles of curcumin: Lessons learned from clinical trials. Advances in Experimental Medicine and Biology, 595-622. https://doi.org/10.1208/s12248-012-9432-8
Healthline. (n.d.). Ayurvedic treatment for PCOS. https://www.healthline.com/health/womens-health/ayurvedic-treatment-for-pcos
Hoeger, K. M., Kochman, L., Wixom, N., Craig, K., Miller, R. K., Guzick, D. S.. (2004). Lifestyle modification in women with PCOS. Fertility and Sterility, 81(3), 632-638. https://doi.org/10.1016/j.fertnstert.2004.02.104
Javed, Z., Papageorgiou, M., Deshmukh, H., Kilpatrick, E. S., Atkin, S. L., Sathyapalan, T.. (2021). Effects of newer pharmacological therapies in PCOS. Journal of Clinical Medicine, 10(5), 1-12. https://doi.org/10.1111/cen.13968
Jensterle, M., Kravos, N. A., Pfeifer, M., Kocjan, T., Janez, A.. (2015). Short-term intervention with liraglutide improved weight management in obese PCOS patients. Endocrine Connections, 4(2), 66-72. https://doi.org/10.3109/07435800.2014.966385
Katore, V., Bhingare, A.. (2024). Phytochemical interventions for PCOS: Systematic review. International Journal of Innovative Science and Research Technology.
Lad, V.. (1999). Textbook of Ayurveda: Fundamental principles.
Legro, R. S., Arslanian, S. A., Ehrmann, D. A., Hoeger, K. M., Murad, M. H., Pasquali, R., et al.. (2013). Diagnosis and treatment of PCOS: An endocrine society clinical practice guideline. Journal of Clinical Endocrinology & Metabolism, 98(12), 4565-4592. https://doi.org/10.1210/jc.2013-2350
Legro, R. S., Brzyski, R. G., Diamond, M. P., Coutifaris, C., Schlaff, W. D., Casson, P., et al.. (2014). Letrozole versus clomiphene for infertility in PCOS. New England Journal of Medicine, 371(2), 119-129. https://doi.org/10.1056/nejmoa1313517
Lim, S. S., Davies, M. J., Norman, R. J., Moran, L. J.. (2012). Overweight and obesity in women with PCOS. Human Reproduction Update, 18(6), 618-637. https://doi.org/10.1093/humupd/dms030
Lord, J. M., Flight, I. H., Norman, R. J.. (2003). Metformin in PCOS. BMJ, 327(7421), 951-953. https://doi.org/10.1136/bmj.327.7421.951
March, W. A., Moore, V. M., Willson, K. J., Phillips, D. I., Norman, R. J., Davies, M. J.. (2010). Prevalence of PCOS in a community sample. Human Reproduction, 25(2), 544-551. https://doi.org/10.1093/humrep/dep399
Mishra, L. C.. (2004). Scientific basis for Ayurvedic therapies.
Moin, A. S., Butler, A. E.. (2019). GLP-1 receptor agonists in PCOS treatment. Frontiers in Endocrinology, 10, 1-7.
Moran, L. J., Hutchison, S. K., Norman, R. J., Teede, H. J.. (2013). Lifestyle changes in women with PCOS. Human Reproduction Update, 19(2), 171-183. https://doi.org/10.1002/14651858.cd007506
Moran, L. J., Pasquali, R., Teede, H. J., Hoeger, K. M., Norman, R. J.. (2009). Treatment of obesity in PCOS. Endocrine, 36(1), 12-20. https://doi.org/10.1016/j.fertnstert.2008.09.018
Nestler, J. E.. (2008). Metformin for the treatment of polycystic ovary syndrome. Journal of Clinical Endocrinology & Metabolism, 93(11), 3993-3999. https://doi.org/10.1210/jcem.86.3.7352-9
Nidhi, R., Padmalatha, V., Nagarathna, R., Amritanshu, R.. (2012). Effect of yoga program on PCOS. Journal of Alternative and Complementary Medicine, 18(10), 1-7. https://doi.org/10.4103/0973-6131.98223
Palomba, S., Falbo, A., Zullo, F., Orio, F.. (2009). Metformin in PCOS management. Endocrine Reviews, 30(1), 1-50. https://doi.org/10.1210/er.2008-0030
Papaetis, G. S., Papakyriakou, P., Panagiotou, T. N.. (2021). Role of incretin-based therapies in metabolic disorders. Hormones, 20(1), 13-24.
Pasquali, R., Stener-Victorin, E., Yildiz, B. O., Duleba, A. J., Hoeger, K. M., Mason, H., et al.. (2011). PCOS research today and tomorrow. Clinical Endocrinology, 74(4), 424-433. https://doi.org/10.1111/j.1365-2265.2010.03956.x
Rasmussen, C. B., Lindenberg, S.. (2014). The effect of GLP-1 receptor agonists on weight and metabolic parameters in PCOS. Diabetes, Obesity and Metabolism, 16(1), 87-91. https://doi.org/10.1111/dom.71179
Rosenfield, R. L., Ehrmann, D. A.. (2016). The pathogenesis of polycystic ovary syndrome: The hypothesis of PCOS as functional ovarian hyperandrogenism revisited. Journal of Clinical Endocrinology & Metabolism, 101(1), 21-31.
Rotterdam ESHRE/ASRM-Sponsored PCOS Consensus Workshop Group. (2004). Revised consensus on diagnostic criteria and long-term health risks related to polycystic ovary syndrome. Human Reproduction, 19(1), 41-47.
Sharma, P. V.. (2010). Dravyaguna vijnana. Chaukhamba Bharati Academy.
Singh, N., Bhalla, M., de Jager, P., Gilca, M.. (2011). An overview on Ashwagandha: A Rasayana herb of Ayurveda. Indian Journal of Psychological Medicine, 33(2), 124-129. https://doi.org/10.4314/ajtcam.v8i5s.9
Singh, R. H.. (2010). Exploring issues in the development of Ayurvedic research methodology. AYU, 31(1), 91-95. https://doi.org/10.4103/0975-9476.65067
Sirmans, S. M., Pate, K. A.. (2014). Epidemiology, diagnosis and management of PCOS. Clinical Epidemiology, 6, 1-13. https://doi.org/10.2147/clep.s37559
Tan, S., Hahn, S., Benson, S., Janssen, O. E., Dietz, T., Kimmig, R., et al.. (2007). Metformin improves pregnancy outcomes in PCOS. Fertility and Sterility, 87(6), 1275-1281.
Tang, T., Lord, J. M., Norman, R. J., Yasmin, E., Balen, A. H.. (2012). Insulin-sensitizing drugs for PCOS. Cochrane Database of Systematic Reviews, 5, CD003053. https://doi.org/10.1002/14651858.cd003053.pub2
Teede, H., Deeks, A., Moran, L.. (2010). Psychological implications of PCOS. Human Reproduction, 25(3), 544-551.
Teede, H. J., Misso, M. L., Costello, M. F., Dokras, A., Laven, J., Moran, L., et al.. (2018). International evidence-based guideline for the assessment and management of PCOS. Clinical Endocrinology, 89(1), 51-72. https://doi.org/10.1111/cen.13795
Tillu, G., Chaturvedi, S., Chopra, A., Patwardhan, B.. (2015). Public health approach of Ayurveda in PCOS. Journal of Ayurveda and Integrative Medicine, 6(3), 197-201.
Unfer, V., Carlomagno, G., Dante, G., Facchinetti, F.. (2017). Effects of myo-inositol in women with PCOS: A systematic review. International Journal of Endocrinology, 2017, 1-9. https://doi.org/10.3109/09513590.2011.650660
World Health Organization. (2023). Polycystic ovary syndrome (PCOS): Global prevalence and health impact. WHO.